
Laser Therapy – Class IV Laser
At VASTA, we use a Class IV Laser. Class IV lasers may also be referred to in some academic literature as High-Intensity Laser Therapy (HILT).
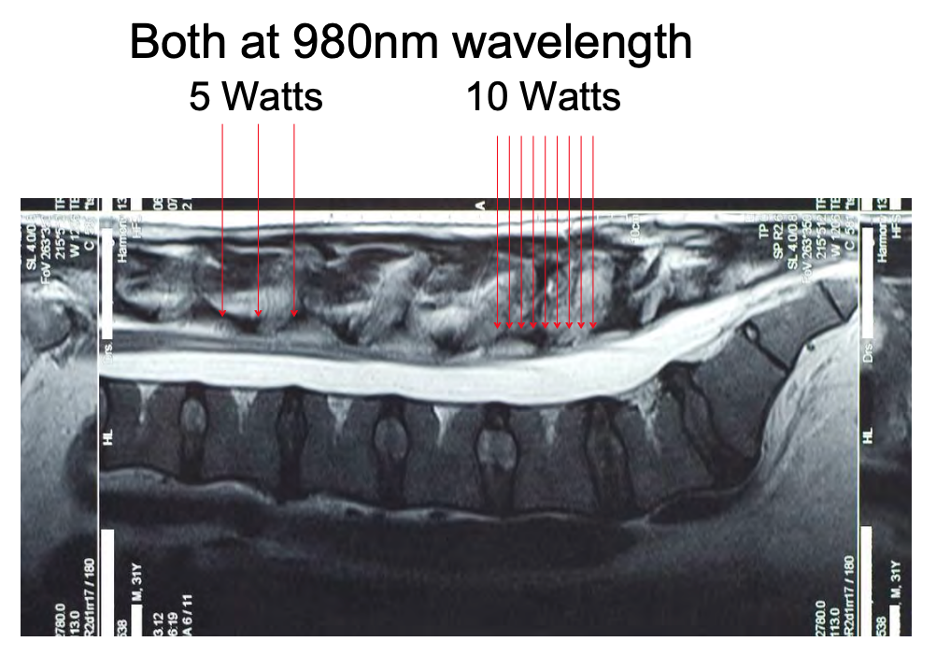
Class IV lasers are defined by a power output exceeding 0.5 Watts (500 mW).
Unlike Class IIIb lasers (“Low-Level Laser Therapy” or LLLT), Class IV lasers use longer infrared wavelengths (900-1064nm) to deliver higher energy doses to deep-seated structural tissues like fascia, muscles, tendons, ligaments, and joints.

In the academic literature, the preferred scientific term for Laser Therapy is Photobiomodulation (PBM)… don’t be fooled, this is the same thing.
For the sake of this summary, we will simplify to ‘Laser Therapy’.
* Note – The research is supportive of Laser Therapy, particularly the use of class IV Lasers, as lower powered lasers have a less robust effect and are not capable of reaching most tissues below the surface.
** Class IV Lasers are very expensive FDA devices.
*** The Laser used in VASTA is a Class IV Laser ***
History of use & Research
Class IV Lasers received FDA clearance in 2004
2008 – World Health Organization (WHO) Task force on Neck Pain and Its Disorders endorsed the use of Laser Therapy. “Laser therapy is beneficial in treatment of neck pain”.
2009 – The American Physical Therapy Association (APTA) made its first official research-based recommendation for the use of Laser therapy (for Achilles tendinopathy).
More recommendations from the APTA followed – Neck Pathology in 2017, Ankle Sprains in 2021, Plantar Fasciitis in 2023, etc.
2012 – International Association for the Study of Pain (IASP) publishes position paper endorsing laser therapy for the treatment of Myofascial Pain
2017 – American College of Physicians (ACP) recommends laser for Chronic LBP
* Laser Therapy was the only modality listed/endorsed.
HOW does it work?
The technical answer – “Photobiomodulation (PBM) is the mechanism by which nonionizing optical radiation from lasers and noncoherent sources in the visible and near – infrared spectral range are absorbed by endogenous chromophores to elicit photophysical and photochemical events at various biological scales, leading to physiological changes and therapeutic effects.” 11
The short answer – Photobiomodulation (PBM) is the process by which optical radiation (specifically dosed light waves within and outside the visual field) stimulates a bio-chemical response in our living tissues.

Some detail – The therapeutic effect of Class IV lasers relies on three primary biological reactions:
- Photobiomodulation: Light energy is absorbed by cellular photoacceptors (primarily cytochrome c oxidase in the mitochondria). This triggers a spike in adenosine triphosphate (ATP) synthesis, accelerating cellular repair, DNA/RNA production, and tissue regeneration. 12
- Anti-Inflammatory & Anti-Edema Effects: HILT suppresses pro-inflammatory cytokines while increasing local microcirculation and angiogenesis (new blood vessel formation), which flushes out cellular waste and reduces swelling. 13 14 15 16 17
- Photothermal Effects: Because of their higher power, Class IV lasers produce a mild, controlled thermal effect in deep tissue. This heat increases local vascularity, relaxes muscle spasms, and immediately disrupts local pain signals (nociceptive nerve conduction). 18 19 20 21 22 23
Effect on Pain & Inflammation

Effect on Tissue Repair / Regeneration

DOES it work? Review of effectiveness in the literature.
Systematic reviews and clinical trials consistently demonstrate that Class IV laser therapy is highly effective for reducing short-to-medium-term pain and restoring functional range of motion.
While early literature is marred with research including ineffective dosages and/or under powered (Not Class IV) Lasers… Quality studies of Class IV Lasers show effectiveness with:
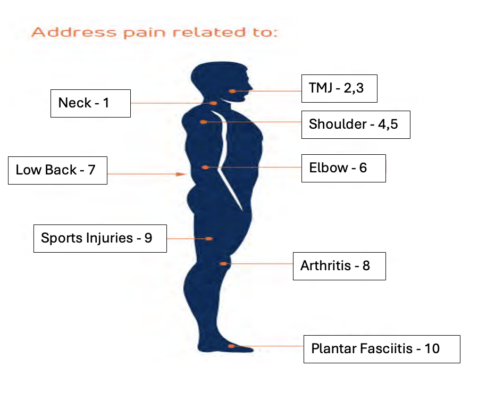
- Ankle Pain / Ankle sprains
- Achilles Tendinitis / Tendinopathy
- Heel Pain / Plantar Fasciitis
- Knee OA (for pain reduction)
- Low Back Pain (chronic)
- Rotator Cuff related pain
- Frozen Shoulder (for decreasing pain during ‘freezing phase’ [first ~ 3 months+/-])
- Lateral Epicondylitis / Tennis Elbow
- Carpal Tunnel
- Neck Pain (multiple types/origins)
Lower powered devices, and devices without A) the capacity to put out the optimal wavelengths (and adapt this based on the target tissue), and B) sufficient power output, will not show similar therapeutic efficacy. High-quality, high-powered Lasers are expensive FDA approved devices. Do not be fooled by cheap alternatives. Their ability to reach deeper tissues, let alone trigger a therapeutic effect, is questionable at best. Class II or III Lasers – so called “Cold Lasers” are an entirely different thing.
Quality research has looked into higher powered Class III devices to see if they could have a similar therapeutic effect if larger dosages were provided over longer time periods compared to a Class IV Device. The results routinely show that the higher powered devices were superior:
- Dramatic difference (favoring Class IV over III) when treating plantar fasciitis 24
- Significant difference (favoring Class IV over III and over exercise) ) for treatment of carpal tunnel 25
- Similar favorable results over a variety of conditions including the knee and shoulder when Class IV and III device outcomes are compared. 26

- Chow RT, Johnson MI, Lopes – Martins RA, Bjordal JM. Efficacy of low – level laser therapy in the management of neck pain: a systematic review and meta-analysis of randomised placebo or activetreatment controlled trials. Lancet. 2009 Dec 5;374(9705):1897-908. doi: 10.1016/S0140- 6736(09)61522 – 1. Epub 2009 Nov 13. Erratum in: Lancet. 2010 Mar 13;375(9718):894. PMID: 19913903.
- Abbasgholizadeh ZS, Evren B, Ozkan Y. Evaluation of the efficacy of different treatment modalities for painful temporomandibular disorders. Int J Oral Maxillofac Surg. 2020 May;49(5):628 – 635. doi : 10.1016/j.ijom.2019.08.010. Epub 2019 Sep 21. PMID: 31547949.
- Khairnar S, Bhate K, S N SK, Kshirsagar K, Jagtap B, Kakodkar P. Comparative evaluation of lowlevel laser therapy and ultrasound heat therapy in reducing temporomandibular joint disorder pain. J Dent Anesth Pain Med. 2019 Oct;19(5):289 – 294. doi : 10.17245/jdapm.2019.19.5.289. Epub 2019 Oct 30. PMID: 31723669; PMCID: PMC6834715.
- Santamato A, Solfrizzi V, Panza F, Tondi G, Frisardi V, Leggin BG, Ranieri M, Fiore P. Short – term effects of high – intensity laser therapy versus ultrasound therapy in the treatment of people with subacromial impingement syndrome: a randomized clinical trial. Phys Ther . 2009 Jul;89(7):643 – 52.
- Kim SH, Kim YH, Lee HR, Choi YE. Short – term effects of high – intensity laser therapy on frozen shoulder: A prospective randomized control study. Man Ther . 2015 Dec;20(6):751 –7. doi : 10.1016/j.math.2015.02.009. Epub 2015 Mar 2. PMID: 25770420.
- Roberts DB, Kruse RJ, Stoll SF. The effectiveness of therapeutic class IV (10 W) laser treatment for epicondylitis. Lasers Surg Med. 2013 Jul;45(5):311 – 7. doi : 10.1002/lsm.22140. Epub 2013 Jun 3. PMID: 23733499.
- Alayat MS, Atya AM, Ali MM, Shosha TM. Long – term effect of high – intensity laser therapy in the treatment of patients with chronic low back pain: a randomized blinded placebo – controlled trial. Lasers Med Sci. 2014 May;29(3):1065 – 73. doi : 10.1007/s10103 – 013 – 1472 – 5. Epub 2013 Nov 2.
- Song HJ, Seo HJ, Kim D. Effectiveness of high – intensity laser therapy in the management of patients with knee osteoarthritis: A systematic review and meta – analysis of randomized controlled trials. J Back Musculoskelet Rehabil . 2020;33(6):875 – 884. doi : 10.3233/BMR – 191738. PMID: 32831189.
- Takenori A, Ikuhiro M, Shogo U, et al. Immediate pain relief effect of low level laser therapy for sports injuries: Randomized, double-blind placebo clinical trial. J Sci Med Sport. 2016;19(12):980- 983. doi:10.1016/j.jsams.2016.03.006
- Ordahan B, Karahan AY, Kaydok E. The effect of high – intensity versus low – level laser therapy in the management of plantar fasciitis: a randomized clinical trial. Lasers in Medical Science. 2018;33(6):1363 – 1369. doi:https ://doi.org/10.1007/s10103 – 018 – 2497 – 6
- Anders JJ, Lanzafame RJ, Arany PR. Low – level light/laser therapy versus photobiomodulation therapy. Photomed Laser Surg 2015;33:183–184
- Friedman, H, Lubart , R 1911, ‘Nonlinear photobiostimulation : the mechanism of visibleand infrared laser – induced stimulation and reducation of neural excitability and growth’, Laser Therapy, vol.3, no. 1, pp. 15- 18.
- Gladwin, MT, Shiva, S 2009, ‘Shining a light on tissue NO stores: near infrared release of NO from nitrite and nitrosylated hemes’, Journal of Molecular and Cellular Cardiology, vol. 46, no. 1, pp. 1 – 3.
- Graves, PJ, Haas, AF, Isseroff , RR, Rood, PA, Wheeland , RG 1990, ‘Low – energy helium – neon laser irradiation increases the motility of cultured human keratinocytes’, Journal of Investigative Dermatology, vol. 94, pp. 822 – 826.
- Greco M, Marra , E, Moro, L, Passarella, S, Perlino , E, Petragallo , VA, Vacca, RA 2001, ‘Helium – Neon laser irradiation of hepatocytes can trigger increase of the mitochondrial membrane potential and can stimulate c – fos expression in a Ca2+ – dependent manner’, Lasers Surgery and Medicine, vol. 29, no. 5, pp. 433 – 441.
- Karu , T 1995, ‘Mechanisms of interaction of monochromatic visible light with cells’, Proc.SPIE , vol. 2630, pp. 2 – 9
- Pires D, Xavier M, Ara?jo T, Silva JA Jr, Aimbire F, Albertini R. Low – level laser therapy (LLLT; 780 nm) acts differently on mRNA expression of anti – and pro – inflammatory mediators in an experimental model of collagenase – induced tendinitis in rat. Lasers Med Sci. 2011;26(1):85 – 94. doi:10.1007/s10103 – 010 – 0811 – z
- Holanda VM, Chavantes MC, Silva DF, de Holanda CV, de Oliveira JO Jr, Wu X, Anders JJ. Photobiomodulation of the dorsal root ganglion for the treatment of low back pain: A pilot study. Lasers Surg Med. 2016 Sep;48(7):653 – 9.
- Chow R, Armati P, Laakso EL, Bjordal JM, Baxter GD. Inhibitory effects of laser irradiation on peripheral mammalian nerves and relevance to analgesic effects: a systematic review. Photomed Laser Surg. 2011;29(6):365 – 381. doi:10.1089/pho.2010.2928
- Holanda VM, Chavantes MC, Wu X, Anders JJ. The mechanistic basis for photobiomodulation therapy of neuropathic pain by near infrared laser light. Lasers Surg Med. 2017;49(5):516 – 524. doi:10.1002/lsm.22628
- Jimbo , K, Noda, K, Suzuki, K, Yoda, K 1998, ‘Suppressive effects of low – power laser irradiation on bradykinin evoked action potentials in cultured murine dorsal root ganglion cells’, Neuroscience Letters, vol. 240, no. 2, pp. 93 – 96
- Cramond , T, Galligan, JP, Laakso EL, Richardson C 1994, ‘ACTH and Beta – Endorphin levels in response to low level laser therapy for myofascial trigger points’, Laser Therapy, vol. 6, no. 3, pp. 133 – 142.
- Montesinos M 1988, ‘Experimental effects of Low Power Laser in Encephalon and Endorphin Synthesis LASERS’, Journ Eur Med Laser Ass., vol. 1, no. 3, pp. 2 – 7
- Ordahan B, Karahan AY, Kaydok E. The effect of high – intensity versus low – level laser therapy in the management of plantar fasciitis: a randomized clinical trial. Lasers Med Sci. 2018 Aug;33(6):1363- 1369.
- Ezzati K, Laakso EL, Saberi A, Yousefzadeh Chabok S, Nasiri E, Bakhshayesh Eghbali B. A comparative study of the dose – dependent effects of low level and high intensity photobiomodulation (laser) therapy on pain and electrophysiological parameters in patients with carpal tunnel syndrome. Eur J Phys Rehabil Med. 2020;56(6):733 – 740. doi:10.23736/S1973 – 9087.19.05835 – 0
- Ordahan B, Karahan AY, Kaydok E. The effect of high – intensity versus low – level laser therapy in the management of plantar fasciitis: a randomized clinical trial. Lasers Med Sci. 2018 Aug;33(6):1363- 1369.