
Extracorporeal Shockwave Therapy
 Extracorporeal Shockwave Therapy (ESWT) is a technology that was originally developed and utilized to break up kidney stones. This early research and utilization was successful and led (as research so often does) to some “incidental findings” – including, that the patients receiving ESWT demonstrated increased bone density of the adjacent tissues (lumbar vertebrae). This spurred a lot of excitement about potential other uses and since the pioneering urological use studies of the 1970’s and 80’s, much research has gone into investigating potential other uses of ESWT.
Here, we discuss, specifically, therapeutic musculoskeletal (MSK) uses.
While very high energy can break down tissues (like kidney stones), properly titrated doses work to stimulate pro-growth & repair processes in various tissues.
ESWT works through a process called mechanotransduction – which is any ‘mechanical’ stimulus that triggers a bio-chemical response in our living tissues. For an easy example, consider that axial weight bearing (mechanical loads) can stimulate activity in cells that live in our bones (osteoblasts) to secrete new bone-building material.
ESWT uses specifically dosed acoustic energy (Shock-waves) to stimulate a cellular healing response in many types of tissues – including bone, cartilage, tendon, muscle, and ligaments. 1 2
The Biological Mechanisms – HOW does it work?
When acoustic shockwaves pass through injured tissue, they trigger (via mechanotransduction) a cascade of biological responses. 3
Primary ‘responses’ confirmed by the literature include:
- Neoangiogenesis: ECSW has been shown to alter Prostaglandin E2 & PGP levels, and stimulates vascular endothelial growth factor (VEGF) to sprout new blood vessels (improving local circulation)
- Tissue Repair: ECSW has been shown to accelerate protein synthesis, promotes cell proliferation, and shifts inflammatory macrophages from a destructive M1 phenotype to a healing M2 phenotype. Increase in PCNA (known as the “master coordinator of DNA replication and repair”) and alterations in TLR 3 & 4 Proteins
- Analgesia: ECSW can alleviate chronic pain by reducing local Substance P (a pain neurotransmitter) and reducing CGRP (promotor of neurogenic inflammation and pain signal propagation), and can hyper-stimulate nociceptors to effectively “gate” pain signals.
- Inflammation Modulation: ECSW effects NO levels and reduces COX-2 (driver of pain and inflammation ‘cascade’)4 5 6 7


Clinical Effectiveness by Injury Type – WHAT do we think it can help with?
Early research (in the 1990’s) focused largely on Calcific Tendonitis, ‘Heel Spurs’ and Lateral Epicondylitis (‘Tennis Elbow’) – with very high success rates (70-80%). Then, in the 2000’s the research on all sorts of muscular and tendon-related injuries blew up.
Current State of Research – While ECSW Therapy has been shown to be widely effective for many MSK injuries – The research suggests that it’s effectiveness varies somewhat depending on the specific tissue type and pathology involved.
*** Keep in mind, ECSW therapy’s clinical impact is amplified when integrated with traditional rehabilitation approaches such as progressive loading, eccentric overloading, movement re-training, activity modification, manual therapies and stretching/mobility regimens 8***
- Strongest Evidence – Chronic Tendinopathies & Plantar Fasciitis
Tendon disorders with poor natural blood supply respond exceptionally well to shockwaves.9
Large-scale data demonstrates that ESWT significantly decreases pain scores and improves physical function in patients with:
- Plantar Fasciitis / Fasciopathy
- Calcific Tendinopathy of the shoulder (Rotator Cuff) – where high energy is used to fragment calcium deposits
- Lateral Epicondylitis (Tennis Elbow)
- Achilles and Patellar tendinopathies
- Emerging Evidence for Hamstring tendinopathies, Gluteal tendinopathies / Greater trochanter pain syndrome as well as Medial Epicondylitis (Golfer’s Elbow)
- Solid Evidence – Bone Healing Failures
ESWT stimulates osteoblast proliferation and bone morphogenetic proteins (BMP), prompting new bone growth.10 “Fracture Nonunions” (delayed bone healing) show an overall success rate range between 62% and 83%, putting ESWT on par with surgical interventions. 11
*However, responses are far better to hypertrophic nonunions (80–100% success) than atrophic nonunions (23–27%)]
Good evidence exists for the treatment of:
- Medial tibial stress syndrome – MTSS (aka. ‘Shin Splints’)
- Bone stress injuries
- Sesamoiditis
- Delayed Union fractures / bone stress injuries (>3 months of symptoms)
- Non-union fractures / bone stress injuries (>6 months of symptoms)
- Early-Stage Osteonecrosis – In conditions like avascular necrosis of the femoral head, early ESWT can prevent joint collapse and may postpone the need for total joint replacement. 12
- Moderate & Emerging Evidence – Myofascial Pain & Muscle Injuries
While ESWT demonstrates good short-term pain relief for Myofascial Pain Syndrome (MPS) and Trigger Point related pain, its long-term advantages are less clear. Meta-analyses reveal it performs beautifully against placebos but yields comparable outcomes to other conventional modalities like dry needling, laser therapy, or targeted exercise programs. 13
Moderate Evidence exists for the treatment of:
- Low-grade partial patellar tendon tear
- Low-grade partial gluteus medius and minimus tear
- Low-grade partial common extensor tendon tear (elbow)
- Low-grade partial insertional Achilles tendon tear
- Low-grade partial midportion Achilles tendon tear (more mixed results here)
- Low-grade partial proximal hamstring tendon tear
- Partial plantar fascia tear
- Non-calcific rotator cuff tendinopathy
WHICH “Type” – Radial vs. Focused ESWT… Which is ‘better’? And for What?
*** At VASTA, we have BOTH Types ***
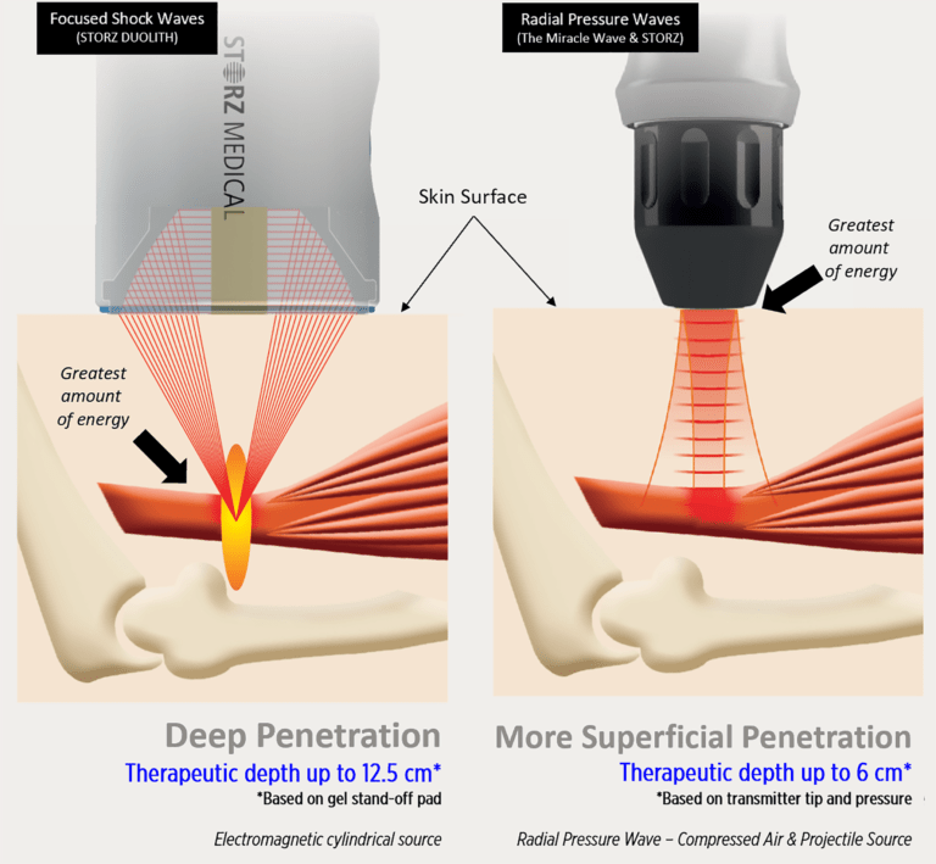
2 ‘Types’ of Shockwave devices are in common use – “Focused Shockwave” Devices and “Radial Pressure Wave” Devices.
These devices utilize different technology and have varying effects. They both, however, leverage the process of mechanotransduction – a ‘mechanical’ stimulus that stimulates a bio-chemical response in our living tissues.
Depth of Tissues being treated is the primary differentiator in deciding which ‘form’ is most appropriate and effective.14

ECSW can work in conjunction with other regenerative therapies – PRP & Stem Cell Injections
Shockwave therapy enhances PRP (platelet-rich plasma) and stem cell treatments by increasing blood flow, stimulating native stem cell activity and migration, and creating a better healing environment for the regenerative cells 15
Some research shows that combining these therapies leads to a faster, more comprehensive recovery, with shockwave providing immediate and long-term pain relief 16
What about Cortisone Steroid Injections?
Cortisone injections are used to reduce inflammation pharmacologically, but they don’t promote tissue healing. In fact, corticosteroids have been shown (particularly with repeated use) to weaken tendons and damage cartilage. Cortisone injections may in fact hinder tissue healing.
Thus, the approach is largely in opposition to what ECSW therapy attempts to do (ie. stimulate tissue rebuilding/remodeling process) That said, there is still a place for the use of corticosteroids – but they should be used sparingly & appropriately.
Though they seem contradictory, there are studies looking at the combination of the two to improve outcomes – however, it is generally advised to wait 4 to 6 weeks after a cortisone injection before initiating shockwave therapy.17 There is some thought that perhaps ECSW can be a counter-balance to the negative effects of corticosteroids. This is only theoretical and has not been specifically clinically tested.
Safety – What are the risks?
While ECSW Therapy does often cause focal micro-trauma, this modality is generally VERY safe.
A few contraindications to utilizing ECSW therapies include:
– No use over a pregnant uterus
– No use over or in the field of a pacemaker
– No use over a known malignant tumor
– No use over active infection
Potential contraindications include:
– Patient has a coagulation disorder or is taking anticoagulant medications
– Patient has a prosthetic device in the area to be treated
– Over ischemic tissue in individuals with vascular disease effects
(ISMST, 2024)
VASTA Pricing and treatment frequency recommendations
Stand-Alone Treatments (not currently being seen for Physical Therapy)
Single – $129
4-Pack – $499
As Add-On Treatments to be performed during/within a scheduled Physical Therapy session (along with your other care/treatment)
Single Add-on $69
4-Pack Add-on $245
- 4-6 Treatments are recommended in the literature
- 4 is likely the ‘minimal effective dose’, although some research shows certain effects (largely the Analgesia effects) are possible with as little as one session
- We typically do not recommend > 6 sessions
- We recommend spacing treatments out ~ 5-7 days. We do not recommend > 10 days in between sessions.
- ’Stacking’ sessions closer together than 5 days is allowed, but may result in slightly less effectiveness overall.
- If you complete a round of 4-6 sessions and want to do a second ‘round’, this is allowed after a 2-3 month wait.
- De la Corte-Rodríguez, H., Román-Belmonte, J. M., Rodríguez-Damiani, B. A., Vázquez-Sasot, A., & Rodríguez-Merchán, E. C. (2023). Extracorporeal Shock Wave Therapy for the Treatment of Musculoskeletal Pain: A Narrative Review. Healthcare, 11(21), 2830. https://doi.org/10.3390/healthcare11212830
- Ryskalin, L. (n.d.). Recent Advances in Shockwave Therapy for Musculoskeletal and Soft-Tissue Disorders
- Moya, D., Ramón, S., Schaden, W., Wang, C.-J., Guiloff, L., & Cheng, J.-H. (2018). The Role of Extracorporeal Shockwave Treatment in Musculoskeletal Disorders. Journal of Bone and Joint Surgery, 100(3), 251-263. https://doi.org/10.2106/jbjs.17.00661
- https://www.sciencedirect.com/science/chapter/bookseries/abs/pii/B9780124200456000031
- https://www.sciencedirect.com/science/article/abs/pii/S0976566220300631
- https://onlinelibrary.wiley.com/doi/abs/10.1002/pros.23880
- https://link.springer.com/article/10.1007/s00193-015-0613-0
- De la Corte-Rodríguez, H., Román-Belmonte, J. M., Rodríguez-Damiani, B. A., Vázquez-Sasot, A., & Rodríguez-Merchán, E. C. (2023). Extracorporeal Shock Wave Therapy for the Treatment of Musculoskeletal Pain: A Narrative Review. Healthcare, 11(21), 2830. https://doi.org/10.3390/healthcare11212830
- Lippi, L., Folli, A., Moalli, S., Turco, A., Ammendolia, A., de Sire, A., & Invernizzi, M. (2024). Efficacy and tolerability of extracorporeal shock wave therapy in patients with plantar fasciopathy: a systematic review with meta-analysis and meta-regression. European Journal of Physical and Rehabilitation Medicine, 60. https://doi.org/10.23736/s1973-9087.24.08136-x
-
Romeo, P., Lavanga, V., Pagani, D., & Sansone, V. (2013). Extracorporeal Shock Wave Therapy in Musculoskeletal Disorders: A Review. Medical Principles and Practice, 23(1), 7-13. https://doi.org/10.1159/000355472
- De la Corte-Rodríguez, H., Román-Belmonte, J. M., Rodríguez-Damiani, B. A., Vázquez-Sasot, A., & Rodríguez-Merchán, E. C. (2023). Extracorporeal Shock Wave Therapy for the Treatment of Musculoskeletal Pain: A Narrative Review. Healthcare, 11(21), 2830. https://doi.org/10.3390/healthcare11212830
- De la Corte-Rodríguez, H., Román-Belmonte, J. M., Rodríguez-Damiani, B. A., Vázquez-Sasot, A., & Rodríguez-Merchán, E. C. (2023). Extracorporeal Shock Wave Therapy for the Treatment of Musculoskeletal Pain: A Narrative Review. Healthcare, 11(21), 2830. https://doi.org/10.3390/healthcare11212830
- Müller-Ehrenberg, H. (n.d.). The State of Extracorporeal Shockwave Therapy for Myofascial Pain Syndrome—A Scoping Review and a Call for Standardized Protocols.
- https://bjsm.bmj.com/content/59/18/1287.abstract
- https://link.springer.com/article/10.1186/s13287-024-03888-w
- https://link.springer.com/article/10.1186/s13287-024-03888-w
- https://onlinelibrary.wiley.com/doi/abs/10.1002/pri.2042